Rajvi Chaudhary, Shaily Saraf.
Department of Pediatrics, Dr. Kiran C. Patel Medical College and Research Institute, Bharuch, Gujarat, India.
ADDRESS FOR CORRESPONDENCE
Rajvi Chaudhary, Dr. Kiran C. Patel Medical College and Research Institute, Bharuch, Gujarat, India.
Email: rajvichaudhary05@gmail.com | | Abstract | | IgA vasculitis (IgAV) is the most common systemic vasculitis of childhood and typically presents with palpable purpura, abdominal pain, arthritis or arthralgia, and renal involvement. We report an 8-year-old girl whose initial presentation was dominated by severe abdominal pain and urticarial lesions, leading to treatment for gastroenteritis with presumed drug-induced urticaria. She subsequently developed bilateral knee pain, burning pain in both feet, edema, acrocyanosis, and palpable purpura of the lower limbs. Examination also revealed prolonged toe capillary refill and initially feeble dorsalis pedis pulses. Laboratory evaluation showed neutrophilic leukocytosis and elevated C-reactive protein, with normal platelet count, coagulation profile, renal function, and urinalysis. Lower-limb Doppler ultrasonography showed no thrombosis. The combination of non-thrombocytopenic purpura, abdominal pain, and arthralgia fulfilled the EULAR/PRINTO/PRES classification framework for IgAV. She improved with supportive care, antihistamine therapy, and oral prednisolone for severe abdominal pain, with restoration of pedal pulses, resolution of edema, and return to ambulation. This case emphasizes that urticaria may precede the characteristic purpura of IgAV and can mimic a drug reaction, particularly when gastrointestinal symptoms occur early. Careful serial skin examination and assessment for multisystem involvement are essential when evaluating children with acute urticaria accompanied by abdominal or musculoskeletal symptoms. Because renal disease may develop after the initial presentation, continued blood pressure and urinalysis surveillance is necessary even when renal investigations are initially normal. The case also demonstrates the importance of not attributing evolving multisystem findings to medication exposure solely because an antihistamine-responsive rash appears early in the illness. | | | | Keywords | | IgA vasculitis, Urticaria, Palpable purpura, Pediatric vasculitis, Abdominal pain. | | | | Introduction | | IgA vasculitis (IgAV), formerly Henoch-Schönlein purpura, is a small-vessel vasculitis with IgA-dominant immune deposition involving the skin, gastrointestinal tract, joints, and kidneys.1,2 Diagnosis is clinical. The EULAR/PRINTO/PRES framework requires purpura or petechiae with lower-limb predominance plus at least one of abdominal pain, arthritis/arthralgia, renal involvement, or IgA-predominant vasculitis on biopsy.3 Although palpable purpura is characteristic, early lesions may be urticarial or maculopapular, creating diagnostic uncertainty.4,5 We describe an 8-year-old girl in whom urticaria preceded palpable purpura and initially suggested a drug reaction. | | | | Case Report | An 8-year-old girl presented with 2 days of severe abdominal pain and vomiting, followed one day later by urticarial lesions over the back and buttocks. She had initially received antispasmodics and antiemetics for presumed acute gastroenteritis. At our center, her parents reported bilateral knee pain and burning pain in both feet severe enough to prevent walking. An upper respiratory tract infection had occurred 10 days earlier.
She was conscious and oriented; heart rate was 130/min and blood pressure 104/68 mmHg. Upper-limb pulses were palpable, whereas dorsalis pedis pulses were initially feeble bilaterally, with prolonged toe capillary refill. Examination showed symmetrical non-blanching petechiae over the lower-limb extensor surfaces, bilateral pedal edema, acrocyanosis of the great toes, and urticarial lesions over the back, buttocks, and thighs. The knees were not swollen and had preserved range of motion, although movement was painful. The abdomen was diffusely tender without guarding or rigidity. (Figure 1)
Figure 1. Palpable Purpura with urticaria.

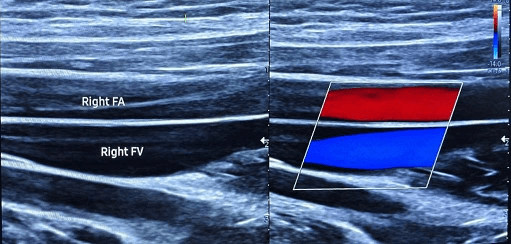
Hemoglobin was 116 g/L, leukocyte count 16.94 × 10^9/L with 84% neutrophils, and platelet count 395 × 10^9/L. C-reactive protein was 74 mg/L, while ESR was 10 mm/h. Renal function, electrolytes, and coagulation studies were normal. Urinalysis showed no hematuria or proteinuria. Abdominal ultrasonography showed minimal free fluid. Because of reduced pedal pulses and prolonged capillary refill, bilateral lower-limb Doppler ultrasonography was performed and showed no thrombosis. An antiphospholipid antibody work-up was advised but could not be completed because of cost constraints. (Figure 2)
Figure 2. Lower limb Doppler USG.
With the appearance of palpable purpura and the combination of abdominal pain and arthralgia, IgAV was diagnosed using the EULAR/PRINTO/PRES framework.3 She received supportive care, including fluids, antiemetics, antispasmodics, lower-limb elevation, and an oral antihistamine. Because of severe abdominal pain, oral prednisolone 1 mg/kg/day was given for 2 weeks and then tapered over 4 weeks.6 The urticaria resolved within 3-4 days. By the second day of steroid therapy, pedal pulses were palpable and edema improved; she became ambulatory by the third hospital day. She was discharged with instructions for serial blood pressure measurement, urinalysis, and pediatric rheumatology follow-up. | | | | Discussion | This case illustrates a diagnostic pitfall: IgAV may initially resemble acute urticaria or a medication reaction. Urticarial or maculopapular lesions may precede typical purpura, and gastrointestinal symptoms may further obscure the diagnosis.4,5 In a child with acute urticaria, severe abdominal pain, arthralgia, dependent edema, or evolving non-blanching lesions should prompt repeated skin examination and consideration of IgAV.
The sequence in this patient was informative: abdominal symptoms and urticaria appeared first, followed by musculoskeletal symptoms and palpable purpura. The antecedent respiratory infection was also compatible with recognized IgAV triggers.1,2 Importantly, normal urinalysis at presentation does not exclude IgAV or eliminate the need for follow-up, because renal involvement can develop after the initial illness.7,8
The EULAR/PRINTO/PRES criteria are useful when the clinical picture evolves, but they are classification criteria rather than a substitute for clinical judgment.3 In atypical rashes or persistent diagnostic uncertainty, skin biopsy with IgA immunofluorescence may be considered.8 In this patient, the progressive appearance of palpable purpura with abdominal pain and arthralgia provided sufficient clinical evidence.
Management is primarily supportive and guided by organ involvement. Current pediatric recommendations support corticosteroids for severe abdominal pain after appropriate assessment for complications such as intussusception.6,9 The improvement observed after prednisolone was favorable, but an individual response cannot establish treatment efficacy. Steroids also do not replace renal surveillance.
Renal involvement is the major determinant of long-term morbidity. Children without renal findings at presentation should undergo continued blood pressure and urinalysis monitoring because nephritis may develop later.7,8,10 Contemporary recommendations support at least 6 months of surveillance, with longer or more intensive follow-up when renal abnormalities occur.7,9 Our patient's normal initial renal evaluation was reassuring but did not end follow-up. | | | | Conclusion | | IgA vasculitis should be considered in children with urticaria when gastrointestinal or musculoskeletal symptoms accompany the rash. Urticaria can precede classic palpable purpura and mimic drug-induced allergy. Serial examination for evolving purpura, careful assessment of abdominal and joint symptoms, and renal surveillance can facilitate timely diagnosis and reduce missed complications. | | | | Compliance with Ethical Standards | | Funding None | | | | Conflict of Interest None | | |
- Song Y, Huang X, Yu G, Qiao J, Cheng J, Wu J, et al. Pathogenesis of IgA vasculitis: an up-to-date review. Front Immunol 2021;12:771619. [CrossRef] [PubMed] [PMC free article]
- Xu L, Li Y, Wu X. IgA vasculitis update: epidemiology, pathogenesis, and biomarkers. Front Immunol 2022;13:921864. [CrossRef] [PubMed] [PMC free article]
- Ozen S, Pistorio A, Iusan SM, et al. EULAR/PRINTO/PRES criteria for Henoch-Schönlein purpura, childhood polyarteritis nodosa, childhood Wegener granulomatosis and childhood Takayasu arteritis: Ankara 2008. Part II: final classification criteria. Ann Rheum Dis 2010;69:798-806. [CrossRef] [PubMed]
- Saulsbury FT. Henoch-Schönlein purpura. Pediatr Dermatol 1984;1:195-201. [CrossRef] [PubMed]
- Reamy BV, Bunt CW, Fletcher S. A diagnostic approach to pruritus. Am Fam Physician 2011;84:195-202.
- Ronkainen J, Koskimies O, Ala-Houhala M, et al. Early prednisone therapy in Henoch-Schönlein purpura: a randomized, double-blind, placebo-controlled trial. J Pediatr 2006;149:241-7. [CrossRef] [PubMed]
- Oni L, Sampath S. Childhood IgA vasculitis (Henoch Schonlein Purpura)-advances and knowledge gaps. Front Pediatr 2019;7:257. [CrossRef] [PubMed]
- Ozen S, Marks SD, Brogan P, et al. European consensus-based recommendations for diagnosis and treatment of immunoglobulin A vasculitis-the SHARE initiative. Rheumatology (Oxford) 2019;58:1607-16. [CrossRef] [PubMed]
- Oni L, Platt C, Marlais M, et al. National recommendations for the management of children and young people with IgA vasculitis: a best available evidence, group agreement-based approach. Arch Dis Child 2024;110:67-76. [CrossRef] [PubMed] [PMC free article]
- Vivarelli M, Samuel S, Coppo R, et al. IPNA clinical practice recommendations for the diagnosis and management of children with IgA nephropathy and IgA vasculitis nephritis. Pediatr Nephrol 2025;40:533-69. [CrossRef] [PubMed] [PMC free article]
DOI: https://doi.org/10.7199/ped.oncall.2027.96
|
| Cite this article as: | | Chaudhary R, Saraf S. When Urticaria Is Not Just an Allergy: A Case of IgA Vasculitis Masquerading as a Drug Reaction. Pediatr Oncall J. 2026 Oct 26. doi: 10.7199/ped.oncall.2027.96 |
|