Daniela Araújo, Mariana Pereira, Joana Vilaça, Joana Oliveira, Ângela Oliveira, Helena Silva
Pediatrics Department, Unidade Local de Saúde de Braga, Braga, Portugal
Address for Correspondence: Daniela Araújo, Sete Fontes - São Victor, 4710-243 Braga, Portugal.
Email: da.niielamatos@hotmail.com
Keywords : parotid abscess, myositis, Bartonella henselae, complicated cat scratch disease
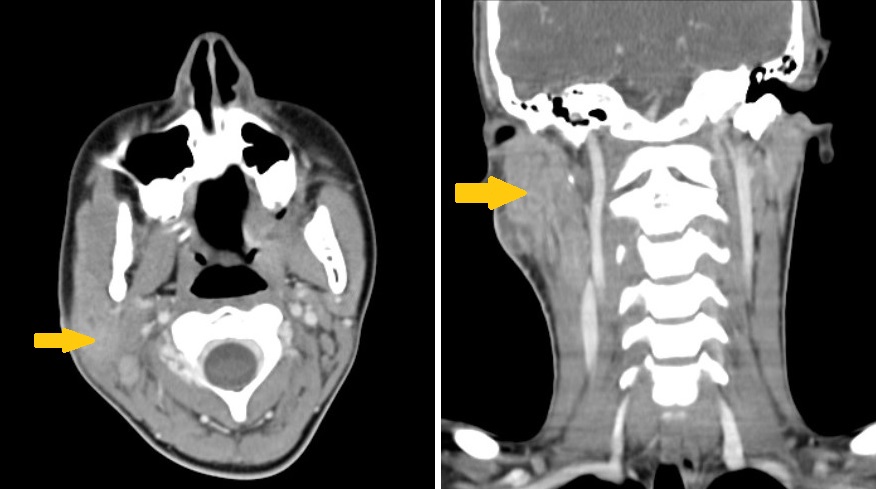
Question: A previously healthy 13-year-old female presented to the Emergency Department (ED) with a painful right cervical mass that had persisted for approximately one month (Figure 1). Initial symptoms included mild odynophagia, which had resolved by the time of admission. The patient denied fever, night sweats, or significant exposure to known infections, although she lived in a rural area with daily contact with a cat and a dog. Her mother had regular contact with a tuberculosis patient at work.
Figure 1. Computerized tomography (CT) findings.
Two weeks prior, her family doctor had ordered blood tests and a cervical ultrasound, which revealed two nodular formations. Despite a 7-day course of oral Amoxicillin with Clavulanic Acid and a 5-day anti-inflammatory regimen, the mass continued to enlarge.
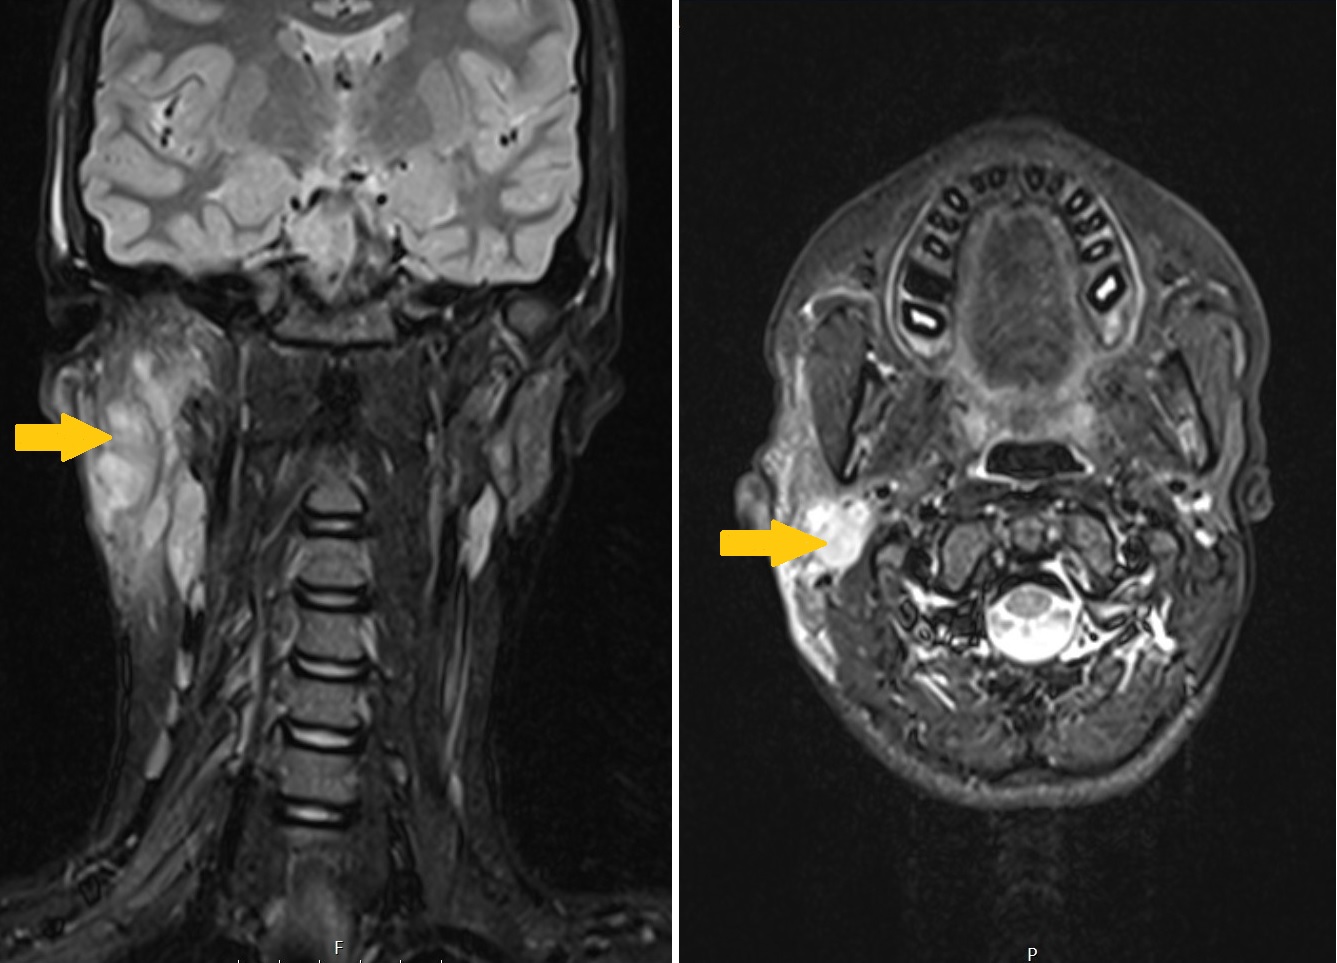
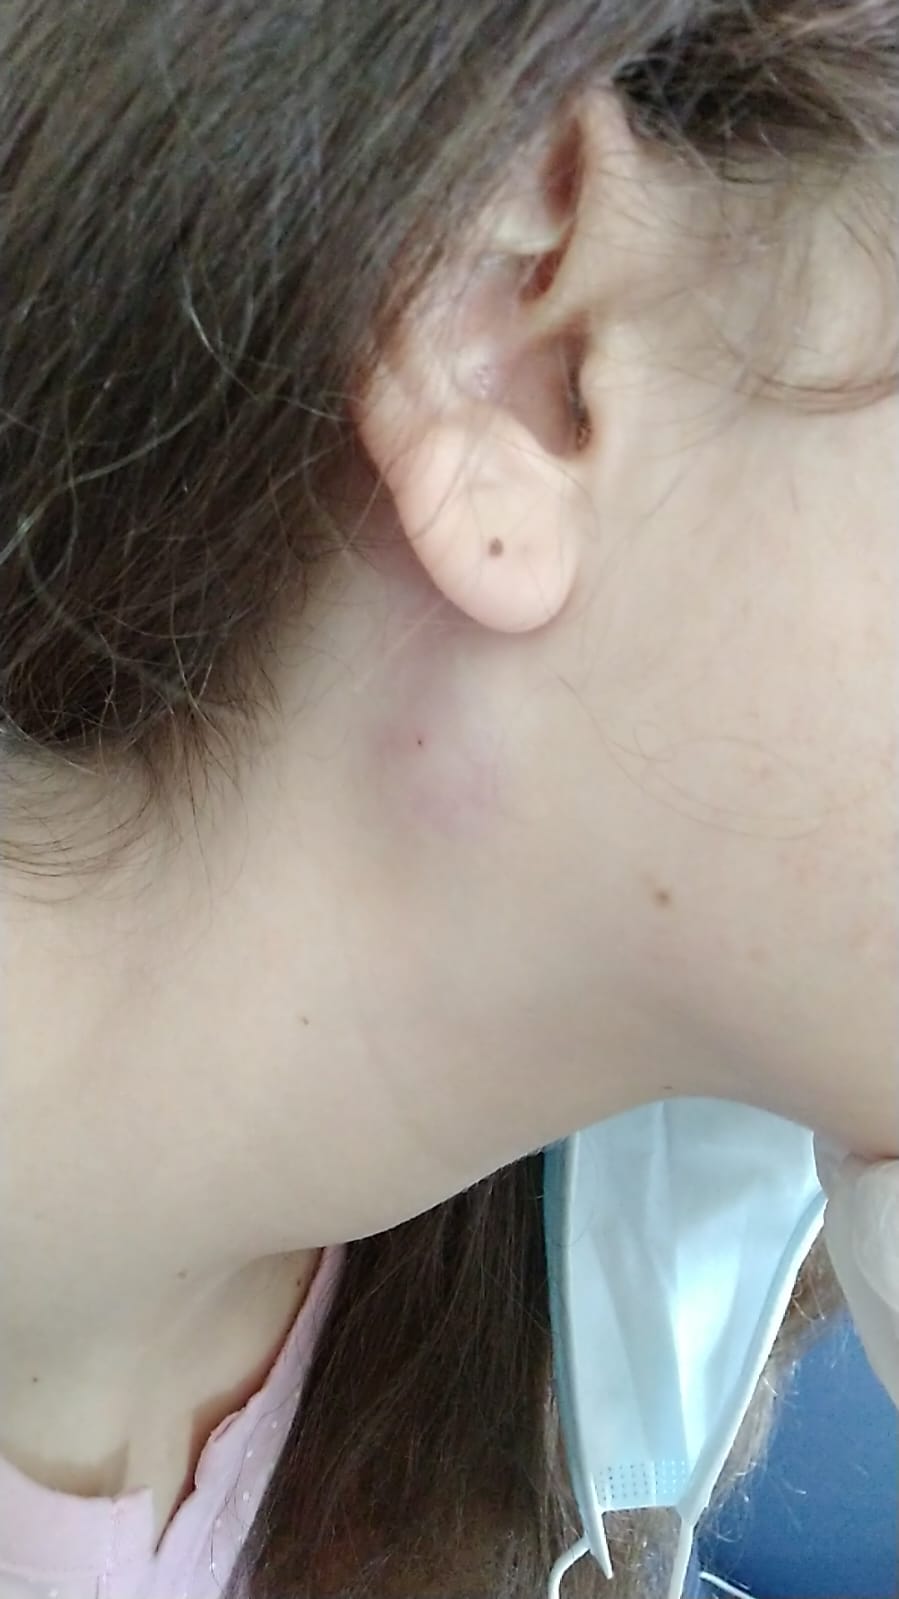
On admission to the ED, a physical exam revealed a 3 cm non-tender, painful cervical swelling with several smaller adjacent swellings. Initial lab results were within normal ranges, and CRP was mildly elevated of 2.1 mg/L (Table 1). A subsequent ultrasound revealed a hypoechogenic mass with irregular contours and surrounding fat hyperechogenicity, suggestive of abscess formation. A cervical CT confirmed a right parotid abscess and ipsilateral platysma myositis (Figure 2).
Table 1. Results from serological testing.
| Serological tests |
Findings |
| Anti-CMV |
Negative (IgG and IgM) |
| EBV early antigen |
Negative for IgG |
| EBV viral capsid antigen |
IgG positive; IgM negative |
| EBV nuclear antigen |
Negative for IgG |
| Herpes simplex 1 |
Negative (IgG and IgM) |
| Herpes simplex 2 |
Negative (IgG and IgM) |
Figure 2. Tumefactions inflammatory signs on the first day of hospitalization.
The patient was started on intravenous ceftriaxone, clindamycin, and oral azithromycin. Despite initial treatment, inflammatory signs worsened. Aspiration was performed and revealed purulent fluid, which was sent for microbiological analysis. MRI confirmed the abscess and surrounding cellulitis (Figure 3). After four days, the patient showed improvement, though the mass persisted, prompting a core biopsy.
Figure 3. Magnetic resonance imaging (MRI) findings.