A case of Clostridioides difficile infection in an infant with COVID-19: A reminder of judicious antibiotic use
Ana Rita Barroca de Macedo1, Beatriz Vilela de Carvalho Taveira Pinto1, Catarina Maria Queirós Fraga1, Sofia Carolina Costa Jordão2, Rui Manuel Correia de Almeida1
1Department of Pediatrics, Hospital Pedro Hispano, Matosinhos, Portugal, 2Department of Infectious Diseases, Hospital Pedro Hispano, Matosinhos, Portugal
Address for Correspondence: Ana Rita Barroca de Macedo, Rua Eduardo Torres, 4464-513 Senhora da Hora, Matosinhos, Portugal.
Email: ritabarrocamacedo@gmail.com
Keywords: Clostridioides difficile, COVID-19, C. difficile toxin, Stool enzyme immunoassay, Vancomycin
Clinical Problem :
A previously healthy seven-month-old female infant presented to the paediatric emergency department with a three-day history of high fever, persistent cough and increased work of breathing. On physical examination, she had polypnea (respiratory rate of 80/min), with pronounced chest wall retractions and bilateral crackles on auscultation, prominent at the right lung base. A nasopharyngeal swab tested positive for SARS-CoV-2 via polymerase chain reaction (PCR).
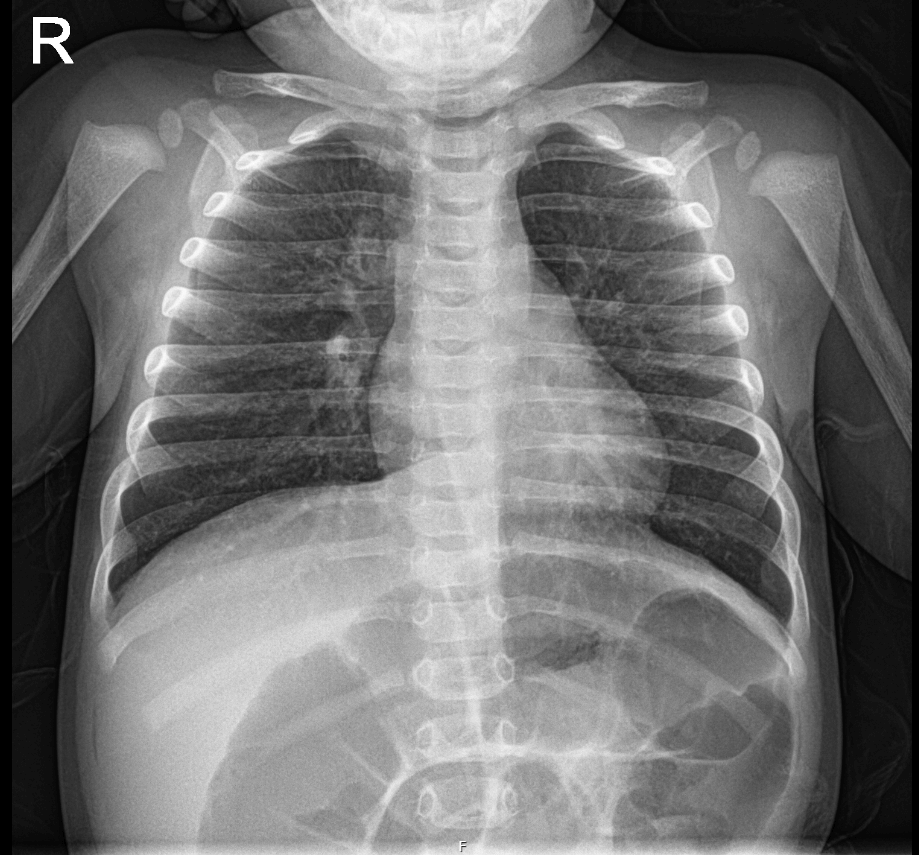
Initial blood tests showed an isolated elevation of C-reactive protein (CRP) to 286 mg/L. Chest radiography revealed bilateral peribronchial markings and decreased transparency in the right pericardiac region, suggestive of COVID-19 pneumonia with possible bacterial superinfection (Figure 1). Intravenous Ampicillin (200 mg/kg/day every 6 hours) was initiated and the patient admitted in our Paediatric facility.
During hospitalization, the infant developed hypoxia, prompting evaluation by the infectious diseases team. Treatment with intravenous remdesivir and Dexamethasone was started per hospital protocol, for five days. Even though respiratory symptoms were resolved by the end of antiviral treatment, patient remained uncomfortable, with increasing food aversion and developed watery and profuse diarrhoea, with over 10 stools per day, without visible blood or mucus, despite feeding modifications and probiotic therapy. On the 9th day of hospitalization, the patient experienced sudden clinical deterioration: hypotension (60/30 mmHg), tachycardia, sunken eyes and fontanelle, dry mucous membranes and lower abdominal tenderness. A 7% weight loss was documented. Laboratory workup revealed hyponatremia (Na? 129 mmol/L), hypokalemia (K? 2.9 mmol/L), leukocytosis (28,000/µL) with neutrophilia and CRP of 16.1 mg/L. Renal function remained normal. She received fluid resuscitation with isotonic crystalloid (20 mL/kg) and maintenance therapy. Stool enzyme immunoassay (EIA) was positive for Clostridioides difficile (C.difficile) toxins A and B. Ampicillin was discontinued and oral Vancomycin (40 mg/kg/day divided every 6 hours) was initiated.
Within 48 hours, the patient showed marked improvement, with reduced stool frequency, improved appetite and better overall appearance. She was discharged on hospital day 15 to complete a 10-day course of oral vancomycin.
Figure 1. Chest radiography at the emergency department showing bilateral peribronchial markings with decreased transparency in the right pericardiac region.
|
In infants hospitalized with viral respiratory infections such as COVID-19, how can clinicians prevent and manage Clostridioides difficile infection effectively?
|
|
|
|
|